TURBT, then chemotherapy or BCG placed in the bladder according to risk group, with regular cystoscopy. CIS counts as high risk.
Home/Conditions/Bladder cancer
Bladder cancer · Robotic radical cystectomy
Robotic surgery for bladder cancer
Robot-assisted radical cystectomy removes the bladder and the pelvic lymph nodes and then builds a new route for urine. It is the standard operation for muscle-invasive bladder cancer. The question that decides treatment is whether the tumour has reached the muscle layer of the bladder wall.
 Written and reviewed by Prof. Dr. Mutlu Ateş, urologist, Antalya American Hospital. More than 1,000 robotic operations. Updated 9 October 2026.
In short
What to know first
- Tumours that stay in the inner layers are usually treated through the urethra (TURBT) and with medicine placed in the bladder. Muscle-invasive disease is treated with radical cystectomy, usually after chemotherapy.
- In the randomised RAZOR trial, two-year progression-free survival was 72.3% after robotic and 71.6% after open surgery: cancer control was equivalent.
- A pooled analysis of 8 randomised trials found less blood loss and fewer transfusions with the robot, a longer operation, and similar complications and quality of life.
- At this practice the bladder is removed with the robot and the urinary diversion is built through a small incision, the method used in RAZOR.
350patients randomised in RAZOR, robotic versus open (Lancet 2018)
338patients in iROC, with fully robotic diversion (JAMA 2022)
1,024patients in the meta-analysis of 8 randomised trials (World J Surg Oncol 2023)
1,063patients in NIAGARA, immunotherapy around surgery (NEJM 2024)
Deciding on treatment
Treatment by tumour depth
From the inside out, the bladder wall has a lining (urothelium), the lamina propria, the muscle layer and the fat around the bladder. How deep the tumour reaches sets the stage and the treatment.
A second resection after TURBT, then BCG. Early cystectomy for selected patients who do not respond to BCG or are at very high risk.
Cisplatin-based chemotherapy before surgery in suitable patients, then radical cystectomy with lymph node dissection. Bladder-preserving trimodal treatment for selected patients.
Systemic treatment before surgery and radical cystectomy. A clear margin and assessment of the lymph nodes are important.
Cystectomy can be performed in selected patients.
Systemic treatment comes first.
The operation
How robotic radical cystectomy is done
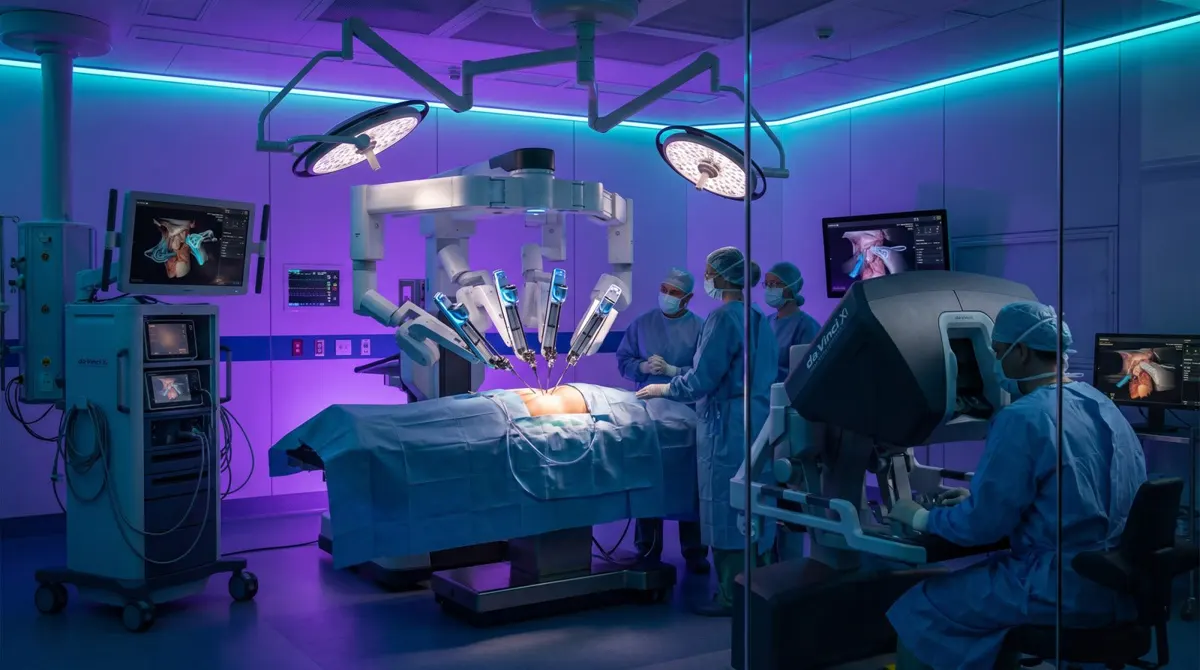
The operation is performed under general anaesthesia with the da Vinci Xi system, in a head-down position. In men the bladder, prostate and seminal vesicles are removed; in selected women the uterus and the front wall of the vagina. In suitable patients nerve-sparing or organ-sparing surgery is possible.
Lymph node dissection
Pelvic lymph nodes are removed on both sides. In the SWOG S1011 trial of 592 patients, a more extended dissection did not improve survival and raised serious side effects (54% versus 44%) and death within 90 days (7% versus 2%). The current approach is a standard dissection.
Urinary diversion inside or outside the body
The new route for urine can be built through a small open incision (extracorporeal) or entirely inside the abdomen with the robot (intracorporeal). The intracorporeal method takes longer and is harder to learn; cancer control is similar. At this practice the bladder is removed with the robot and the diversion is then built through a small incision (extracorporeal).
Ileal conduit (urostomy)
- How it works
- A short piece of small bowel is joined to the ureters and brought out through the abdominal wall as a stoma. Urine drains into a bag.
- Suits
- Older patients, other illnesses, reduced kidney function, or a need for quicker recovery.
- Advantage
- Technically simpler, a shorter operation and fewer long-term problems.
- Needs
- Stoma care, with the site marked and teaching given before surgery.
Neobladder
- How it works
- A reservoir is made from 40 to 60 cm of small bowel and joined to the urethra, so urine is passed the usual way.
- Suits
- Good kidney function, a tumour-free urethral margin, strong motivation, and no previous radiotherapy to the pelvis.
- Advantage
- No stoma and no bag. In published series, daytime continence is reached in 85 to 90% and night-time continence in 60 to 80%.
- Needs
- Voiding training and pelvic floor exercises in the first months.
Evidence
What the studies show
Robotic versus open radical cystectomy
| Measure | Open | Robotic | Source |
|---|---|---|---|
| Progression-free survival at 2 years | 71.6% | 72.3% (equivalent) | RAZOR, randomised |
| Blood loss | Reference | 328 mL less | Meta-analysis, 8 randomised trials |
| Transfusion | Reference | Odds ratio 0.45 | Meta-analysis |
| Operating time | Reference | 84 minutes longer | Meta-analysis |
| Margins, node count, stay, complications, quality of life | Similar | Similar | Meta-analysis |
| Days at home in the first 90 days | 80 | 82 | iROC, randomised |
| Blood clots | 8.3% | 1.9% | iROC, randomised |
| Wound complications | 16% | 5.6% | iROC, randomised |
In RAZOR the diversion was built through an incision, as it is at this practice. In iROC it was built inside the body with the robot, so the iROC figures on blood clots and wound complications cannot be carried over directly. The iROC authors judged the clinical importance of the two-day difference to be uncertain.
Where the robotic approach helps
- Less blood loss. About 328 mL less, with fewer transfusions.
- Equivalent cancer control in the randomised RAZOR trial.
- Sparing surgery. Nerve-sparing in selected men, and uterus, ovary and vagina sparing in selected women.
What to keep in mind
- A longer operation and a higher cost.
- Complications and hospital stay overall are not significantly different from open surgery.
- A clear learning curve, and more technical difficulty after radiotherapy to the pelvis.
- A decision for a team. The plan is made for each patient with urology, medical oncology, radiology and pathology.
After surgery
Recovery after cystectomy
Radical cystectomy is a major operation. Recovery follows an enhanced-recovery programme: information before surgery, early walking, early eating and pain control that limits opioids.

- Day 0 to 1
Walking and clear fluids start early.
- Discharge
Timing depends on the type of diversion, the course of the operation and how recovery goes. No fixed number of days is given in advance.
- Week 2 to 3
Ureteric stents are usually removed. With a neobladder, the catheter comes out at about week 3 after a check for leaks.
- Week 6 to 8
Full daily activity. Continence training and pelvic floor work continue with a neobladder.
For patients from abroad, the length of stay in Antalya is planned individually for this operation.
Questions
Frequently asked questions
What is the difference between muscle-invasive and non-muscle-invasive bladder cancer?
Tumours that stay in the lining or the lamina propria are non-muscle-invasive and are treated through the urethra and with medicine placed in the bladder. Tumours that reach the muscle layer or deeper are muscle-invasive; the European Association of Urology guideline recommends cisplatin-based chemotherapy followed by radical cystectomy for suitable patients.
Is cancer control the same after robotic and open cystectomy?
Yes, in the randomised evidence. In RAZOR, two-year progression-free survival was 72.3% after robotic and 71.6% after open surgery. In the meta-analysis of 8 randomised trials with 1,024 patients, surgical margins, lymph node counts and survival did not differ between the two approaches.
Who is suited to a neobladder?
Patients with good kidney function, a urethral margin free of tumour, strong motivation, and no previous radiotherapy to the pelvis. In the ICUD-EAU consultation, daytime continence was reached in 85 to 90% and night-time continence in 60 to 80%, with poorer results in elderly patients, and training is needed in the first months. Otherwise an ileal conduit is usually the better choice.
Is chemotherapy or immunotherapy needed before surgery?
For muscle-invasive disease in patients fit for cisplatin, chemotherapy before surgery is standard. In the NIAGARA trial of 1,063 patients, adding durvalumab before and after surgery raised two-year event-free survival from 59.8% to 67.8% and overall survival from 75.2% to 82.2%, with a similar rate of serious side effects. The plan is made with medical oncology.
Can the bladder be kept?
In selected patients, yes. Trimodal treatment combines the most complete resection possible through the urethra with chemotherapy and radiotherapy given together. The European Association of Urology guideline accepts it as an alternative to cystectomy for suitable patients and stresses regular cystoscopy afterwards.
How long is the hospital stay after robotic cystectomy?
It varies with the type of urinary diversion, the course of the operation and recovery afterwards, so no fixed number of days is promised in advance. In the iROC trial, patients spent a median of 82 of the first 90 days at home after robotic surgery and 80 after open surgery.
Sources
The studies behind this page
- Parekh DJ, et al. RAZOR. Lancet. 2018;391(10139):2525-2536.
- Catto JWF, et al. iROC. JAMA. 2022;327(21):2092-2103.
- Liu H, et al. Robotic versus open radical cystectomy: meta-analysis. World J Surg Oncol. 2023;21(1):240.
- Lerner SP, et al. Standard or extended lymphadenectomy (SWOG S1011). N Engl J Med. 2024;391(13):1206-1216.
- Powles T, et al. NIAGARA. N Engl J Med. 2024;391(19):1773-1786.
- Hautmann RE, et al. ICUD-EAU International Consultation on Bladder Cancer 2012: urinary diversion. Eur Urol. 2013;63(1):67-80.
- EAU Guidelines on Muscle-invasive and Metastatic Bladder Cancer, 2026.
From the blog
Decision guides on this topic
Other conditions