
What is UPJ obstruction, and what symptoms does it cause in adults?
Ureteropelvic junction (UPJ) obstruction is a narrowing at the point where the kidney's collecting funnel, the renal pelvis, joins the ureter, so that urine leaves the kidney too slowly and the kidney swells. The swelling is called hydronephrosis. In British texts the same condition is called pelvi-ureteric junction (PUJ) obstruction.
There are two main causes, and they can occur together.
- Intrinsic narrowing. A short segment of the ureter wall is stiff or poorly formed and does not pass urine onward as it should. It is present from birth, yet it may cause no trouble until adult life.
- A crossing vessel. An artery or vein on its way to the lower part of the kidney lies across the junction and kinks it. This is common: in one series of 65 laparoscopic pyeloplasties, crossing vessels were found in 42 patients (65%).
Less often the ureter leaves the renal pelvis too high up, or the junction is scarred after stones, infection or earlier surgery.
The typical symptoms in adults are:
- flank pain that comes in bouts, sometimes after drinking a large amount of fluid in a short time;
- repeated urinary infections or a kidney infection with fever;
- kidney stones, which form more easily in urine that stands still;
- blood in the urine;
- no symptoms at all: the swollen kidney is found by chance on an ultrasound or CT scan done for another reason.
This article is about adults. In babies and children the condition is assessed and treated by different rules, and paediatric care is a separate topic.
Which tests show whether UPJ obstruction needs surgery?
Two kinds of test are needed: imaging that shows the anatomy, and a diuretic renogram that shows how well the kidney works and drains. A swollen kidney on a scan does not prove obstruction, because some wide collecting systems still empty well.
| Test | What it shows | Why it matters |
|---|---|---|
| Ultrasound | Whether the kidney is swollen and how thick the kidney tissue is | First test and simple follow-up |
| CT urography or CT angiography | The level of the narrowing, stones and crossing vessels | Planning the operation |
| MR urography | The same anatomy without radiation | An alternative to CT |
| Diuretic renogram (MAG3) | Split function and drainage of each kidney | Shows whether the blockage matters, and is the baseline for later checks |
| Blood and urine tests | Overall kidney function and infection | Safety before surgery |
The renogram gives two results. Split function is the share of total kidney work done by each kidney; two healthy kidneys share the work roughly equally. Drainage is how quickly the tracer leaves the kidney after a diuretic is given. A kidney that holds the tracer back and does a falling share of the work is being harmed by the obstruction.
There is no single cut-off that every centre uses, and studies define their own. As one example, the three-centre robotic series cited below counted a repair as successful when the drainage half-time on the renogram was under 20 minutes and the symptoms had gone.
Cross-sectional imaging sometimes shows something unrelated, such as a kidney mass. That is a different question, covered on the kidney tumours page.
When is pyeloplasty needed, and when is it safe to watch?
Surgery is advised when the obstruction causes symptoms or is harming the kidney; a kidney that is dilated but drains adequately, works well and causes little or no trouble can be watched. The usual reasons to operate are:
- recurring flank pain that fits the obstruction;
- repeated infections;
- stones forming in the obstructed kidney;
- a falling share of function or worsening drainage on repeat renograms;
- increasing dilation on imaging.
Watching is a real option for the right patient. In a single-centre study of 50 patients with no or minimal symptoms, each followed with at least two renograms for a mean of 53 months, 10 deteriorated. Eight of those went on to pyeloplasty and two to removal of the kidney. Every patient whose renogram worsened without symptoms did so within 2 years of diagnosis.
Limits: a small series from one hospital. It supports watching with scheduled repeat renograms, not simply waiting.
What does a dismembered pyeloplasty do, and what happens to a crossing vessel?
The surgeon cuts out the narrowed junction and sews the healthy renal pelvis to the healthy ureter with a wide, funnel-shaped join; a crossing vessel is kept and moved out of the way. "Dismembered" means that the junction is divided completely. The operation is also known as the Anderson-Hynes pyeloplasty, after the surgeons who described it. In plain steps:
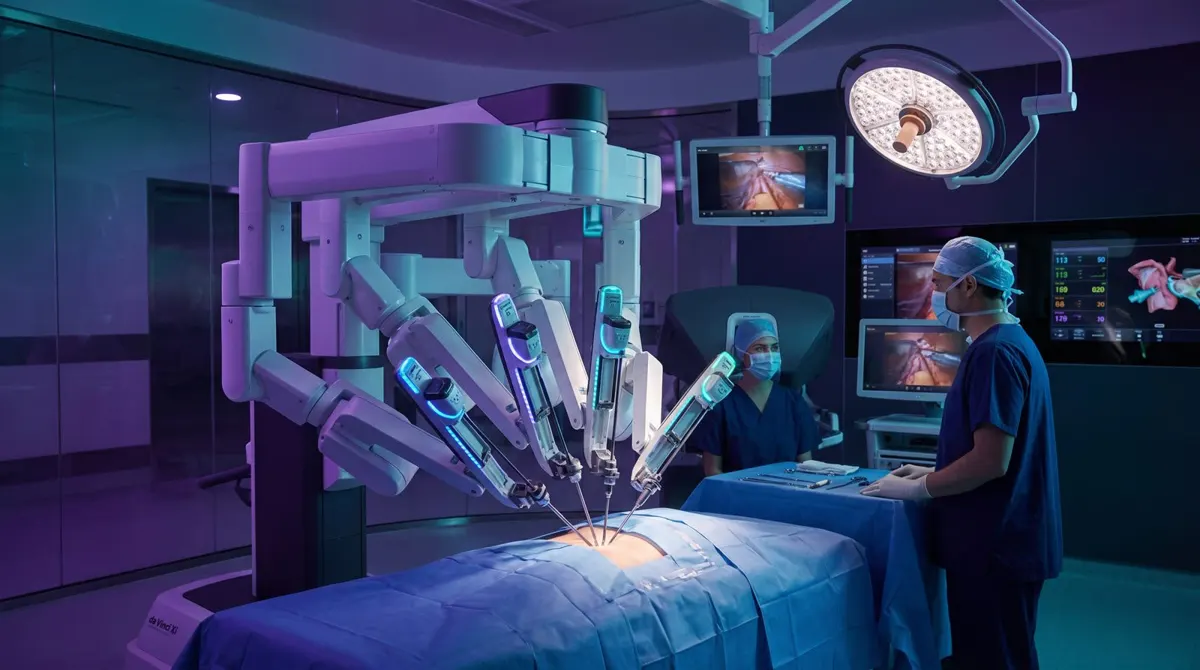
- Access. Under general anaesthesia, a camera and fine instruments are passed through small incisions. In robotic surgery the surgeon controls them from a console beside the patient.
- Exposure. The bowel is moved aside, and the renal pelvis and the upper ureter are freed.
- Finding the cause. The junction is inspected and a crossing vessel is looked for.
- Removing the narrow segment. The junction is cut out. The end of the ureter is opened lengthways so that the new join is wide, and a very baggy renal pelvis may be trimmed.
- Crossing vessel. The vessel is preserved, because it usually supplies part of the kidney. The pelvis and ureter are rejoined in front of it, so that it no longer presses on the junction.
- Stones. Stones lying in the kidney can often be removed in the same operation.
- Suturing. The join is sewn with fine absorbable stitches so that it is watertight and free of tension.
- Stent. A thin internal tube (JJ stent) is placed from the kidney to the bladder to protect the join while it heals.
The crossing vessel is one reason why the cause matters for the choice of treatment. A cut made from inside the ureter cannot move a vessel. In a Mayo Clinic series, 8 of 26 patients (31%) whose endopyelotomy had failed and who then had an open repair were found to have crossing vessels.
Is robotic pyeloplasty better than laparoscopic or open surgery?
All three approaches perform the same repair with similar success; keyhole surgery avoids a large incision, and the robot mainly makes the fine suturing easier. The comparisons rest almost entirely on non-randomised studies.
| Question | Finding | Study |
|---|---|---|
| Open versus keyhole | Similar success and complication rates; in adults a shorter hospital stay with keyhole surgery. | Autorino 2014: systematic review and meta-analysis |
| Robotic versus laparoscopic | Robotic: operating time 27 minutes shorter, stay 1.2 days shorter, lower odds of complications (odds ratio 0.56), higher odds of success (odds ratio 2.76). Evidence quality low to very low. | Light 2018: meta-analysis of 17 observational studies |
| Robotic, medium term | Success 97.6% at a mean of 39 months; complications 6.6%; mean operating time 134.9 minutes; mean stay 1.5 days. | Sivaraman 2012: 168 adults, 3 centres |
| Robotic, long term | Success in 125 of 129 (96.9%); 8-year failure-free survival 91.5%. | Hopf 2016: 129 cases, one centre |
| Laparoscopic, with late failures | Success 88% at 1 year and 83% in the long term; major complications 14%, all urine leakage or blockage. | Madi 2008: 65 consecutive cases, one centre |
Limits: the 17 studies in the meta-analysis were all observational and 10 were judged to be of low quality. Its authors were unsure whether the statistical differences mean a real difference for patients. The case series are retrospective, and each defined success in its own way.
Prof. Dr. Mutlu Ateş operates at Antalya American Hospital with the da Vinci Xi system and has performed more than 1,000 robotic operations in total (prostate, kidney, bladder and adrenal).
What robotic pyeloplasty offers
- No large incision. The repair is done through small incisions with a magnified view.
- High success in published series. 97.6% in 168 adults at a mean of 39 months, and an 8-year failure-free survival of 91.5% in another series.
- Short hospital stay. A mean of 1.5 days in the three-centre series.
- The cause is treated. The narrow segment is removed, a crossing vessel is moved, and stones can be taken out in the same operation.
What it costs
- It is a full operation. General anaesthesia, then a stent for some weeks and a short procedure to remove it.
- Complications occur. 6.6% in the series of 168 adults. Urine leakage or blockage at the join is the typical problem.
- Stent discomfort. Urgency, frequent urination and flank ache are common while it is in place.
- Not permanent for everyone. In one laparoscopic series, failures appeared at 2, 2.5 and 6 years.
- The evidence is mostly non-randomised. The advantage over laparoscopy is statistical and of uncertain size.
Is endopyelotomy or balloon dilation a reasonable alternative to pyeloplasty?
They are lighter procedures with a lower and less durable success rate, so they suit selected patients rather than most. In endopyelotomy the narrowing is cut open from inside, either with a scope passed up the ureter or through a small track in the back. In balloon dilation it is stretched. Neither removes the narrow segment, and neither can deal with a crossing vessel.
| Comparison | Result | Study |
|---|---|---|
| Antegrade endopyelotomy versus pyeloplasty | Recurrence-free at 3, 5 and 10 years: 63%, 55% and 41% versus 85%, 80% and 75%. | Dimarco 2006: 182 and 175 patients |
| Balloon dilation versus laparoscopic pyeloplasty | Success at 6 months: 86.8% versus 97.7%. At 24 months: 71.0% versus 95.5%. | Xu 2016: 38 and 44 patients |
Limits: both studies are retrospective and from single centres. The Mayo series covers 1988 to 2004, its pyeloplasties were open or laparoscopic, and success required improvement on imaging and in symptoms. In the balloon study, patients chose their treatment after counselling and all had a narrowing shorter than 2 cm.
The less invasive route is reasonable to discuss when the narrowing is short, no crossing vessel is seen, the kidney is not greatly dilated and still works well, or when a longer operation carries more risk for you. The balloon procedure was quicker and the hospital stay shorter in that study. The price is a higher chance of needing a further procedure.
How long do the stent, the hospital stay and recovery take?
Most patients leave hospital within a few days, keep the internal stent for some weeks and return to normal activity step by step. Reported hospital stays differ between hospitals and health systems: a mean of 1.5 days in the three-centre series of robotic pyeloplasty, a median of 2 days in a laparoscopic series, and 5 and 6 days in the two arms of a Swiss randomised trial.
The stent. That Swiss trial randomised 100 patients having laparoscopic or robotic pyeloplasty to a stent for 1 week or 4 weeks. Success was 100% and 98%, and complications occurred in 4% and 6%. One trial from one centre does not settle the question, and many surgeons still leave the stent for several weeks, so the duration is set individually. The stent is removed through the bladder with a thin camera, as a short procedure that does not need another operation.
While the stent is in place, a frequent and urgent need to pass urine, an ache in the flank when you pass urine and pink urine are common. Fever or strong pain should be reported.
- First days. You walk early. A bladder catheter, and a drain if one was placed, are usually removed before you go home.
- First weeks. Light activity and desk work are possible. Heavy lifting and strenuous sport are avoided, and you should drink well.
- After stent removal. Exercise is built up gradually, and the first check of drainage is planned.

If you come from abroad. Your reports and images are reviewed first by WhatsApp or email, and the surgery day is set from the test results before you fly. The day before surgery you meet the surgeon, have the anaesthesia assessment and sign consent; the operation is the next day. Plan 5 to 7 days in Antalya in total. The stent will usually still be in place when you leave. It can be removed at home by a urologist or on a return visit: agree this with the surgeon before you book, and arrange the urologist at home in advance. If the anaesthesia assessment finds a serious condition that was not declared, surgery may be postponed.
How is success checked, and can the narrowing come back?
Success means two things together: the symptoms have gone and a repeat scan shows that the kidney drains. The narrowing can return, usually early but sometimes years later. The check is usually an ultrasound after the stent is out and a diuretic renogram some months later. In the Swiss trial, for example, patients had contrast X-rays at 3 months, a renogram at 6 months and ultrasound at 1, 3 and 5 years.
On late failures, three sources agree:
- In the Mayo series most failures happened within 2 years, but new ones kept appearing after 5 and 10 years.
- In a series of 65 laparoscopic pyeloplasties, 7 of the 60 patients with follow-up (12%) failed within 1 year, and 3 more who had seemed cured returned at 2, 2.5 and 6 years. All failures caused symptoms.
- In 129 robotic pyeloplasties followed for a mean of 33.8 months, the estimated 8-year failure-free survival was 91.5%.
There is no agreed schedule for how long formal follow-up should last. The practical rule is simple: flank pain or a kidney infection on the operated side, even years later, is a reason for a scan.
What if a previous repair failed, or the kidney already works poorly?
A failed repair can usually be repaired again, and a weak kidney is not removed automatically; both situations need a more careful assessment.
Redo pyeloplasty. A meta-analysis of 15 studies with 1,637 patients compared first-time minimally invasive pyeloplasty (1,371 patients) with redo surgery (266 patients). Hospital stay and overall complications did not differ significantly. First-time repairs were shorter by a mean of 36.91 minutes, lost a mean of 16.70 mL less blood, leaked urine less often and had a modestly higher success rate (relative risk 1.07). In the three-centre robotic series, 21 of the 168 operations (12.5%) were redo repairs, and the authors considered the robotic approach suitable for both. All of these data are observational. When scarring leaves no usable renal pelvis, other reconstructions exist, and the choice is made case by case.
A poorly functioning kidney. Removal is discussed when the kidney contributes very little, keeps causing pain or infection, and the other kidney is healthy. It is not the only path. In a retrospective study of 63 adults whose obstructed kidney did 15% or less of the total work, 19 had laparoscopic pyeloplasty and 44 had the kidney removed. Symptoms resolved in 73% and 76% of the two groups, with no significant difference. The repaired kidneys did not gain function (a mean share of 9.5% before and 10% after), but they did not lose it either. The study is small and short-term. What daily life and follow-up look like after losing a kidney is described in living with one kidney.
Which questions should you ask your surgeon?
Ask what your own scans show, and what would happen without surgery.
- What is the split function of my kidney, and does the renogram show obstruction or only dilation?
- Is there a crossing vessel on my imaging?
- Would watching with repeat renograms be safe for me, and what would make you change that advice?
- Why do you recommend pyeloplasty rather than endopyelotomy or balloon dilation, or the reverse?
- How long will the stent stay, and who will remove it?
- Which scans will show that the repair has worked, and when?
- If it fails, what are the next options?
This article gives general information and does not replace an assessment of your own scans and results. Treatment is decided individually.